

The Best Vein Treatment for Your Patients
At Aleman Vein Center, we consider it a great honor that you would consider us to assist in the care of your patients. We truly strive to be the best source of medical vein care in the Greater Atlanta area. In addition, we aim to make your patients happy that you cared enough to send them our way.
We deliver with our focus on clinical excellence and care delivered in a respectful and empathetic manner. To us, your patient and their vein disease is our priority. Nothing else comes first.
Dr. Chad Aleman has 20 years of experience in the diagnosis and management of venous insufficiency and has personally performed thousands of outpatient venous procedures during that time. Dr. Aleman is Diplomate of The American Board of Venous & Lymphatic Medicine. He has also earned ultrasound credentials, including the Registered Physician in Vascular Interpretation (RPVI) and Registered Vascular Technologist (RVT).
Dr. Aleman has previously held leadership positions as a member of the Medical Executive Committee and a Regional Medical Director for Vein Clinics of America with clinical supervision over multiple other vein clinics. He has trained and supervised multiple other vein specialists, advanced practice providers, sonographers and nurses in the care of patients with venous disease.
Aleman Vein Center is Accredited by the Intersocietal Accreditation Commission (IAC) for Vascular Testing. This is the highest standard for facilities that perform diagnostic ultrasound and is recommended for all medical practices that treat venous disease by both the American Vein & Lymphatic Society and Society of Vascular Surgery. All of our ultrasound technologists are Registered Vascular Technologists (RVT) by the ARDMS.
Our practice is solely dedicated to the care of your patients with venous disease and that will not take a back seat to anything. Veins are not an “add-on” or ancillary service in our practice. We do not spend the bulk of our time treating unrelated issues, such as arterial disease, or performing hospital-based interventional procedures. As such, we are able to perform a more comprehensive work-up and treatment plan individualized to each patient. If your patient has been told they “don’t have anything wrong” when you suspect venous problems or they don’t improve as expected after treatment, we would be happy to see them for a second opinion. We can usually get to the bottom of the issue with a thorough patient history, physical exam, and in-office ultrasound.
We are a local, physician-owned practice. We focus on what is in the best interests of your patients.

Call (404) 777-1728 to Schedule a patient
Fax referrals to
(833) 471-4351


How to Recognize the Patient Who Would Benefit from Vein Treatment
Dr. Aleman’s article from Atlanta Medicine - Journal of the Medical Association of Atlanta, 2023, Vol. 94, No. 6
Click HERE for pdf version.
A Frequently Misunderstood Disease
“You’re the 4th doctor I’ve been to about this discoloration on my ankle, and nobody seems to know what it is.” Unfortunately, this is a common statement that I have heard over the years in my vein practice from patients with severe chronic venous insufficiency. Although venous disease is incredibly common, patients and many physicians still have the misperception that venous disease is merely a cosmetic issue. This delay in diagnosis often leads to a significant quality of life impact and puts some patients at risk for complications such as venous stasis ulcerations, thrombophlebitis, cellulitis, and secondary lymphedema.
A Common Affliction
Approximately one-third of men and women develop varicose veins and nearly half of those have been shown to deteriorate within 13 years to skin changes with risks of ulceration. (Ref 1,2) Approximately 500,000 venous ulcers occur each year in the U.S. affecting 1-3% of the population, and most leg ulcers have a venous cause. (Ref 3)
New Referral Patterns Needed for Venous Leg Ulcers
While venous ulcers are generally preventable with treatment at earlier disease stages, they remain common. Unfortunately, most patients never get treatment of their venous insufficiency and are often treated with compression and/or wound care. Recent clinical trials have proven that venous ulcers heal faster with an estimated cost savings of $5,226 per patient when immediately referred for early treatment of the venous disease. (Ref 3,4) Venous leg ulcers also have a lower rate of recurrence when the underlying venous reflux is treated. (Ref 5)
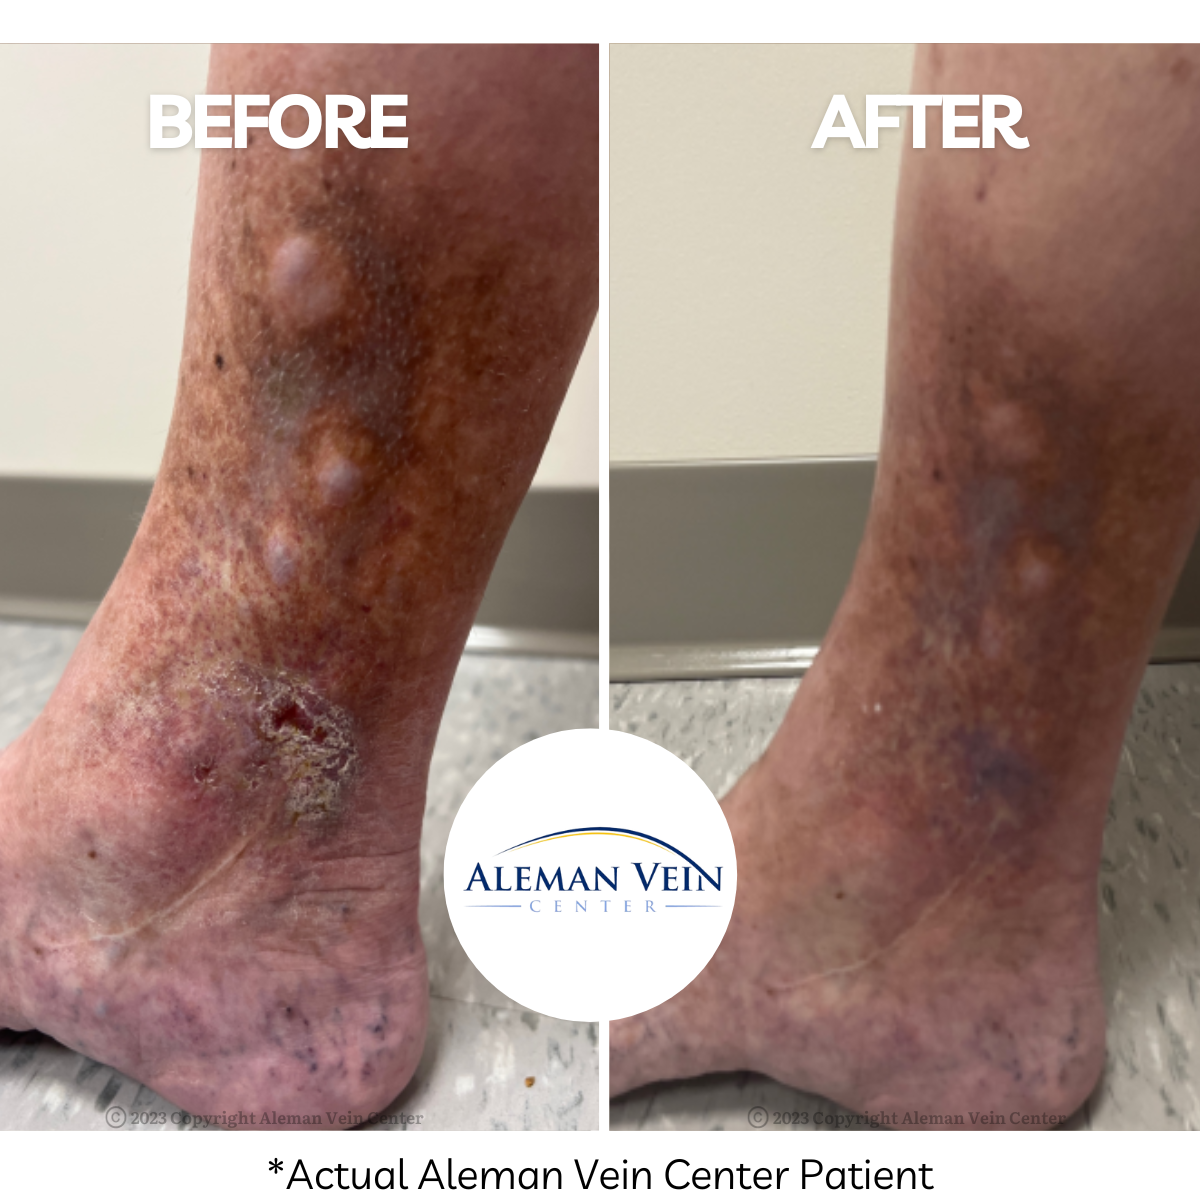
All patients with venous stasis ulcerations should be referred to a vein specialist for treatment of the wound’s causative factor upon diagnosis of the wound. While concurrent referral to a wound center may be indicated, referral for vein treatment should not be delayed pending the outcome of a trial of compression or wound care as early venous intervention improves healing times and saves costs. The patient in Figure 1 healed within 4 weeks of venous procedures.
Figure 1 - Patient with venous ulcer healed within 4 weeks of venous treatment.
Which Other Patients May Benefit
In my practice, most patients with severe complications such as ulcers, severe skin changes, or bleeding have had multiple encounters with other physicians and discussed their venous disease, but the opportunity for intervention was missed.
The most common mistake that I encounter is that patients are simply asked, “Do those veins bother you?” The patient typically replies that they don’t find them concerning because they assume that the physician is asking whether they are bothered by the cosmetic appearance of their veins. Patients also tend to mistake venous symptoms as a normal part of aging, due to weight gain, or caused by the type of floors that they stand on all day at work.
Upon encountering visible evidence of venous disease, a more effective approach is to try to elicit specific symptoms with questions such as:
Do you experience aching, pain, heaviness, or fatigue in the legs at the end of the day or with prolonged sitting or standing?
Do you have cramps in the legs or feet waking you at night?
Do you feel like you have to move your legs around to get comfortable when you are trying to go to sleep?
Do you have swelling in your ankles at the end of the day or with prolonged sitting?
It is important to keep venous disease in your differential when evaluating leg complaints. The symptoms of venous insufficiency are usually worse later in the day, worse with prolonged standing or sitting, and improve with leg elevation. In women, the symptoms are often worse in the premenstrual phase of the menstrual cycle and during pregnancies. The symptoms are typically diffuse below the knee and often described as a vague aching, heaviness, fatigue, or uncomfortable feeling. Nocturnal cramps and restlessness in the leg and feet are also typical complaints related to venous insufficiency.
Dermatologic findings of venous insufficiency are often missed or the significance minimized as they may indicate pre-ulcerative skin changes. Patients with venous stasis dermatitis (Figure 2) may be confused with recurrent cellulitis. The rash is typically erythematous, pruritic, and located around the ankles. When visible varicosities are present, the diagnosis is usually clear. However, stasis dermatitis should be considered when the rash is bilateral, other constitutional symptoms such as fevers and chills are absent, or the rash is unresponsive to antibiotics. Although venous stasis dermatitis may improve with topical steroids, it is a symptom of venous insufficiency which should be more definitively addressed.
Figure 2 - Classic location of venous stasis dermatitis at the medial malleolus. The rash is often confused with cellulitis.
Hyperpigmentation may result from hemosiderin or iron staining and typically occurs just proximal to the ankle. Lipodermatosclerosis is a sunken deformity just above the ankle which frequently is indurated with a brown or red discoloration. In a severe form, the lower leg takes on the appearance of an inverted champagne bottle. Atrophie blanche (“white atrophy”) appears as a white, depressed, stellate shaped plaque typically occurring around the ankles. These skin changes may be indicators that there is a risk for ulceration and the patient would benefit from evaluation. The patient in Figure 3 is a good example of bilateral hyperpigmentation. On his left leg, there is one large and one small ulceration along with atrophie blanche.
Modern, minimally-invasive treatment options for venous insufficiency such as radiofrequency ablation, ultrasound-guided foam sclerotherapy, ambulatory phlebectomy, and adhesive ablation are safe, effective, and can be completed in an office setting without the need of sedation.
Like many diseases that we treat in medicine, venous insufficiency is chronic and progressive. Although treatment does not result in a permanent cure, it can greatly improve your patients’ quality of life while preventing severe complications of the disease. If patients do have recurrent symptoms or skin changes, that usually does not represent a treatment failure. The patient may simply have disease progression with new sources of venous reflux that require additional treatment in order to maintain control of their underlying chronic disease.
REFERENCES:
Evans CJ, Fowkes FG, Ruckley CV, Lee AJ. Prevalence of varicose veins and chronic venous insufficiency in men and women in the general population: Edinburgh Vein Study. J Epidemiol Community Health. 1999 Mar;53(3):149-53. doi: 10.1136/jech.53.3.149. PMID: 10396491; PMCID: PMC1756838.
Lee AJ, Robertson LA, Boghossian SM, Allan PL, Ruckley CV, Fowkes FG, Evans CJ. Progression of varicose veins and chronic venous insufficiency in the general population in the Edinburgh Vein Study. J Vasc Surg Venous Lymphat Disord. 2015 Jan;3(1):18-26. doi: 10.1016/j.jvsv.2014.09.008. Epub 2014 Nov 1. PMID: 26993676
Gohel MS, Heatley F, Liu X, Bradbury A, Bulbulia R, Cullum N, Epstein DM, Nyamekye I, Poskitt KR, Renton S, Warwick J, Davies AH; EVRA Trial Investigators. A Randomized Trial of Early Endovenous Ablation in Venous Ulceration. N Engl J Med. 2018 May 31;378(22):2105-2114. doi: 10.1056/NEJMoa1801214. Epub 2018 Apr 24. PMID: 29688123.
Zheng H, Magee GA, Tan T, Armstrong DG, Padula WV. Cost-effectiveness of Compression Therapy With Early Endovenous Ablation in Venous Ulceration for a Medicare Population. JAMA Netw Open. 2022;5(12):e2248152. doi:10.1001/jamanetworkopen.2022.48152
Gohel MS, Barwell JR, Taylor M, Chant T, Foy C, Earnshaw JJ, Heather BP, Mitchell DC, Whyman MR, Poskitt KR. Long term results of compression therapy alone versus compression plus surgery in chronic venous ulceration (ESCHAR): randomised controlled trial. BMJ. 2007 Jul 14;335(7610):83. doi: 10.1136/bmj.39216.542442.BE. Epub 2007 Jun 1. PMID: 17545185; PMCID: PMC1914523.

Visual Cues for Patients that Should be Referred for an Evaluation at Aleman Vein Center
Note that skin findings and leg swelling can occur without obvious varicose veins.

Corona Phlebectatica - this fan shaped cluster of spider veins usually indicates underlying reflux in the great saphenous vein when seen at the medial malleolus and the small saphenous vein when seen at the lateral malleolus.
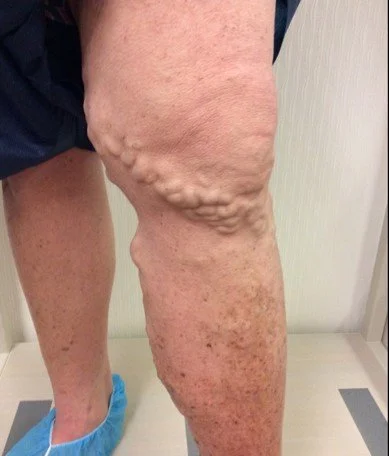
Note the skin hyperpigmentation and swelling in the calf.

If it looks like BILATERAL cellulitis, it is probably venous stasis dermatitis.

Severe venous insufficiency with hyperpigmentation, lipodermatosclerosis, and small venous stasis ulceration.

Lipodermatosclerosis causes a sunken appearance with thickened skin. The calf frequently appears much larger due to swelling that is trapped above the subcutaneous fibrosis. In severe cases, the lower leg takes on the shape of an “upside down champagne bottle.”

Atrophie Blanche or white atrophy
The typical location of venous stasis dermatitis and other skin changes is just proximal to the medial malleolus due to the anatomical relationship to the distal great saphenous vein.

Severe venous insufficiency with hyperpigmentation, lipodermatosclerosis and risk for ucleration.

Venous stasis ulcer - This is not a disease and should not be treated with wound care alone - this is a complication of venous disease. Treatment of the underlying venous insufficiency can speed healing and help to prevent recurrence. Referral for evaluation and treatment should be considered mandatory for all patients with venous ulcerations, both active and healed.